ESMO26: Roche's KRAS drug tops approved drugs in NSCLC

Ferdinandos Skoulidis of MD Anderson Cancer Center, presenting the Krascendo-1 data at ESMO.
In the Krascedo-1 trial, Roche's KRAS G12C inhibitor divarasib met the company's high expectations, with a head-to-head win over Amgen's Lumakras and Bristol Myers Squibb's Krazati.
The open-label study compared divarasib to Lumakras (sotorasib) and Krazati (adagrasib) in 338 people with previously treated KRAS G12C-mutated non-small cell lung cancer (NSCLC) who had not been exposed to prior treatment with a KRAS or RAS inhibitor.
The verdict? Roche's drug scored higher on progression-free survival (PFS), overall survival (OS), and objective response rate (ORR) compared to its rivals, showing the potential to improve on the first-generation KRAS inhibitors.
Most compellingly, divarasib achieved a 44% improvement in OS – something that has not been achieved with the older drugs – with a median duration of 17.7 months versus 12 months for the control group.
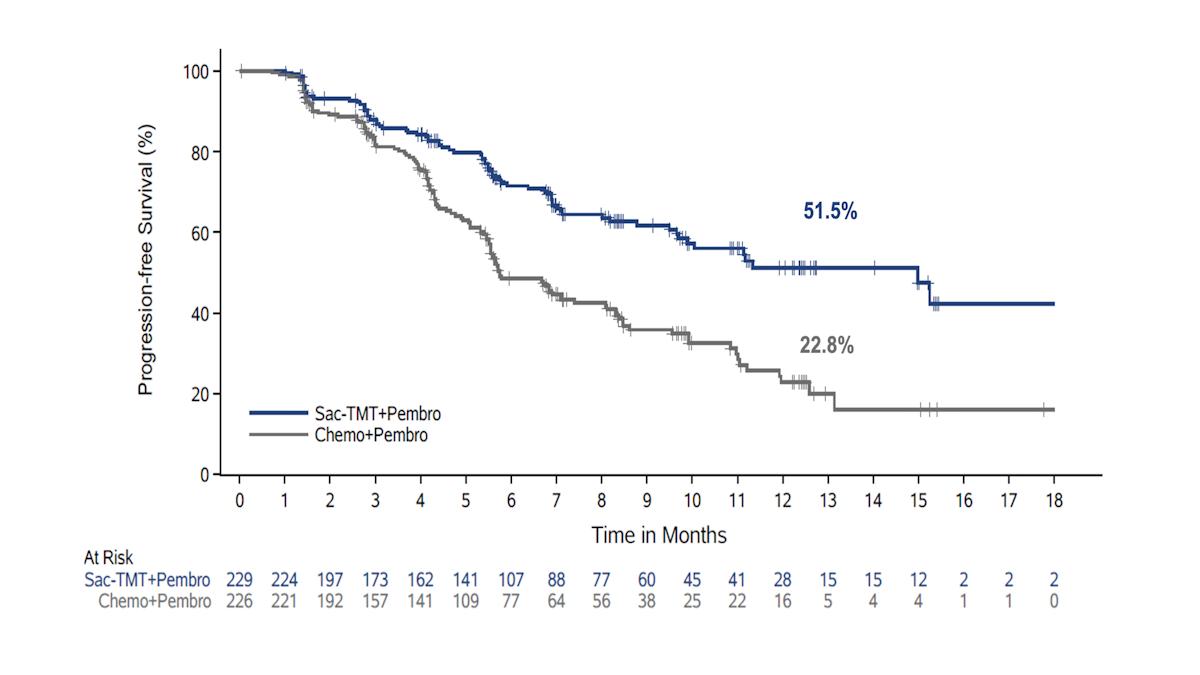
PFS, the primary endpoint, came in at 9.8 months and 5.7 months, respectively, giving an improvement of 42% with divarasib, while confirmed ORR was also 25.8% better. After 12 months, 44% of the divarasib group were alive without disease progression, compared to 24% of patients on Lumakras or Krazati.
The results – which have also been published in the New England Journal of Medicine – "highlight divarasib's practice-changing potential," said lead investigator Ferdinandos Skoulidis, of MD Anderson Cancer Centre in the US.
"New life-extending treatments are greatly needed, as most patients with this type of cancer will eventually relapse after initial therapy, and there are limited effective treatments for recurrent disease," he added.
Roche is running a phase 3 trials programme for divarasib as both a monotherapy and as a chemo-free combination across various cancers and lines of therapy. Krascendo-2 is comparing the drug plus MSD's Keytruda (pembrolizumab) to Keytruda and chemo as a first-line therapy for KRASG12C-mutated NSCLC, while Krascendo-3 is comparing divarasib to immunotherapy as adjuvant therapy for earlier-stage disease.
"Despite the early excitement surrounding sotorasib and then adagrasib, their efficacy is only limited and an OS benefit against chemotherapy has not been demonstrated," said ESMO commentator Prof Benjamin Besse, of Institut Gustave Roussy in France.
"Results from Krascendo-1 trial indicate that the higher potency of divarasib could translate into a new standard of care," he added, whilst also applauding the tolerability of the new drug overall – there were more gastrointestinal side effects than with Lumakras, however – and a low tendency to stimulate resistance mutations.
KRAS G12C mutations occur in approximately 13% of people with NSCLC, the most common form of lung cancer.
Lumakras and Krazati were the first KRAS-targeted drugs to reach the market, after decades of research into what was once considered an "undruggable" target, but have so far failed to match that scientific achievement commercially, with sales staying fairly modest in their current second-line indications.
Their potential has been held back by narrow patient populations, problems with drug resistance, reimbursement hurdles and, at least initially, limited access to KRAS testing.
Divarasib is one of several 'second-generation' KRAS inhibitors hoping to capture market share and grow the market for the class, along with MSD's calderasib and Eli Lilly's olomorasib, which are also in phase 3.