Unlocking the scalability of allogeneic CAR-T
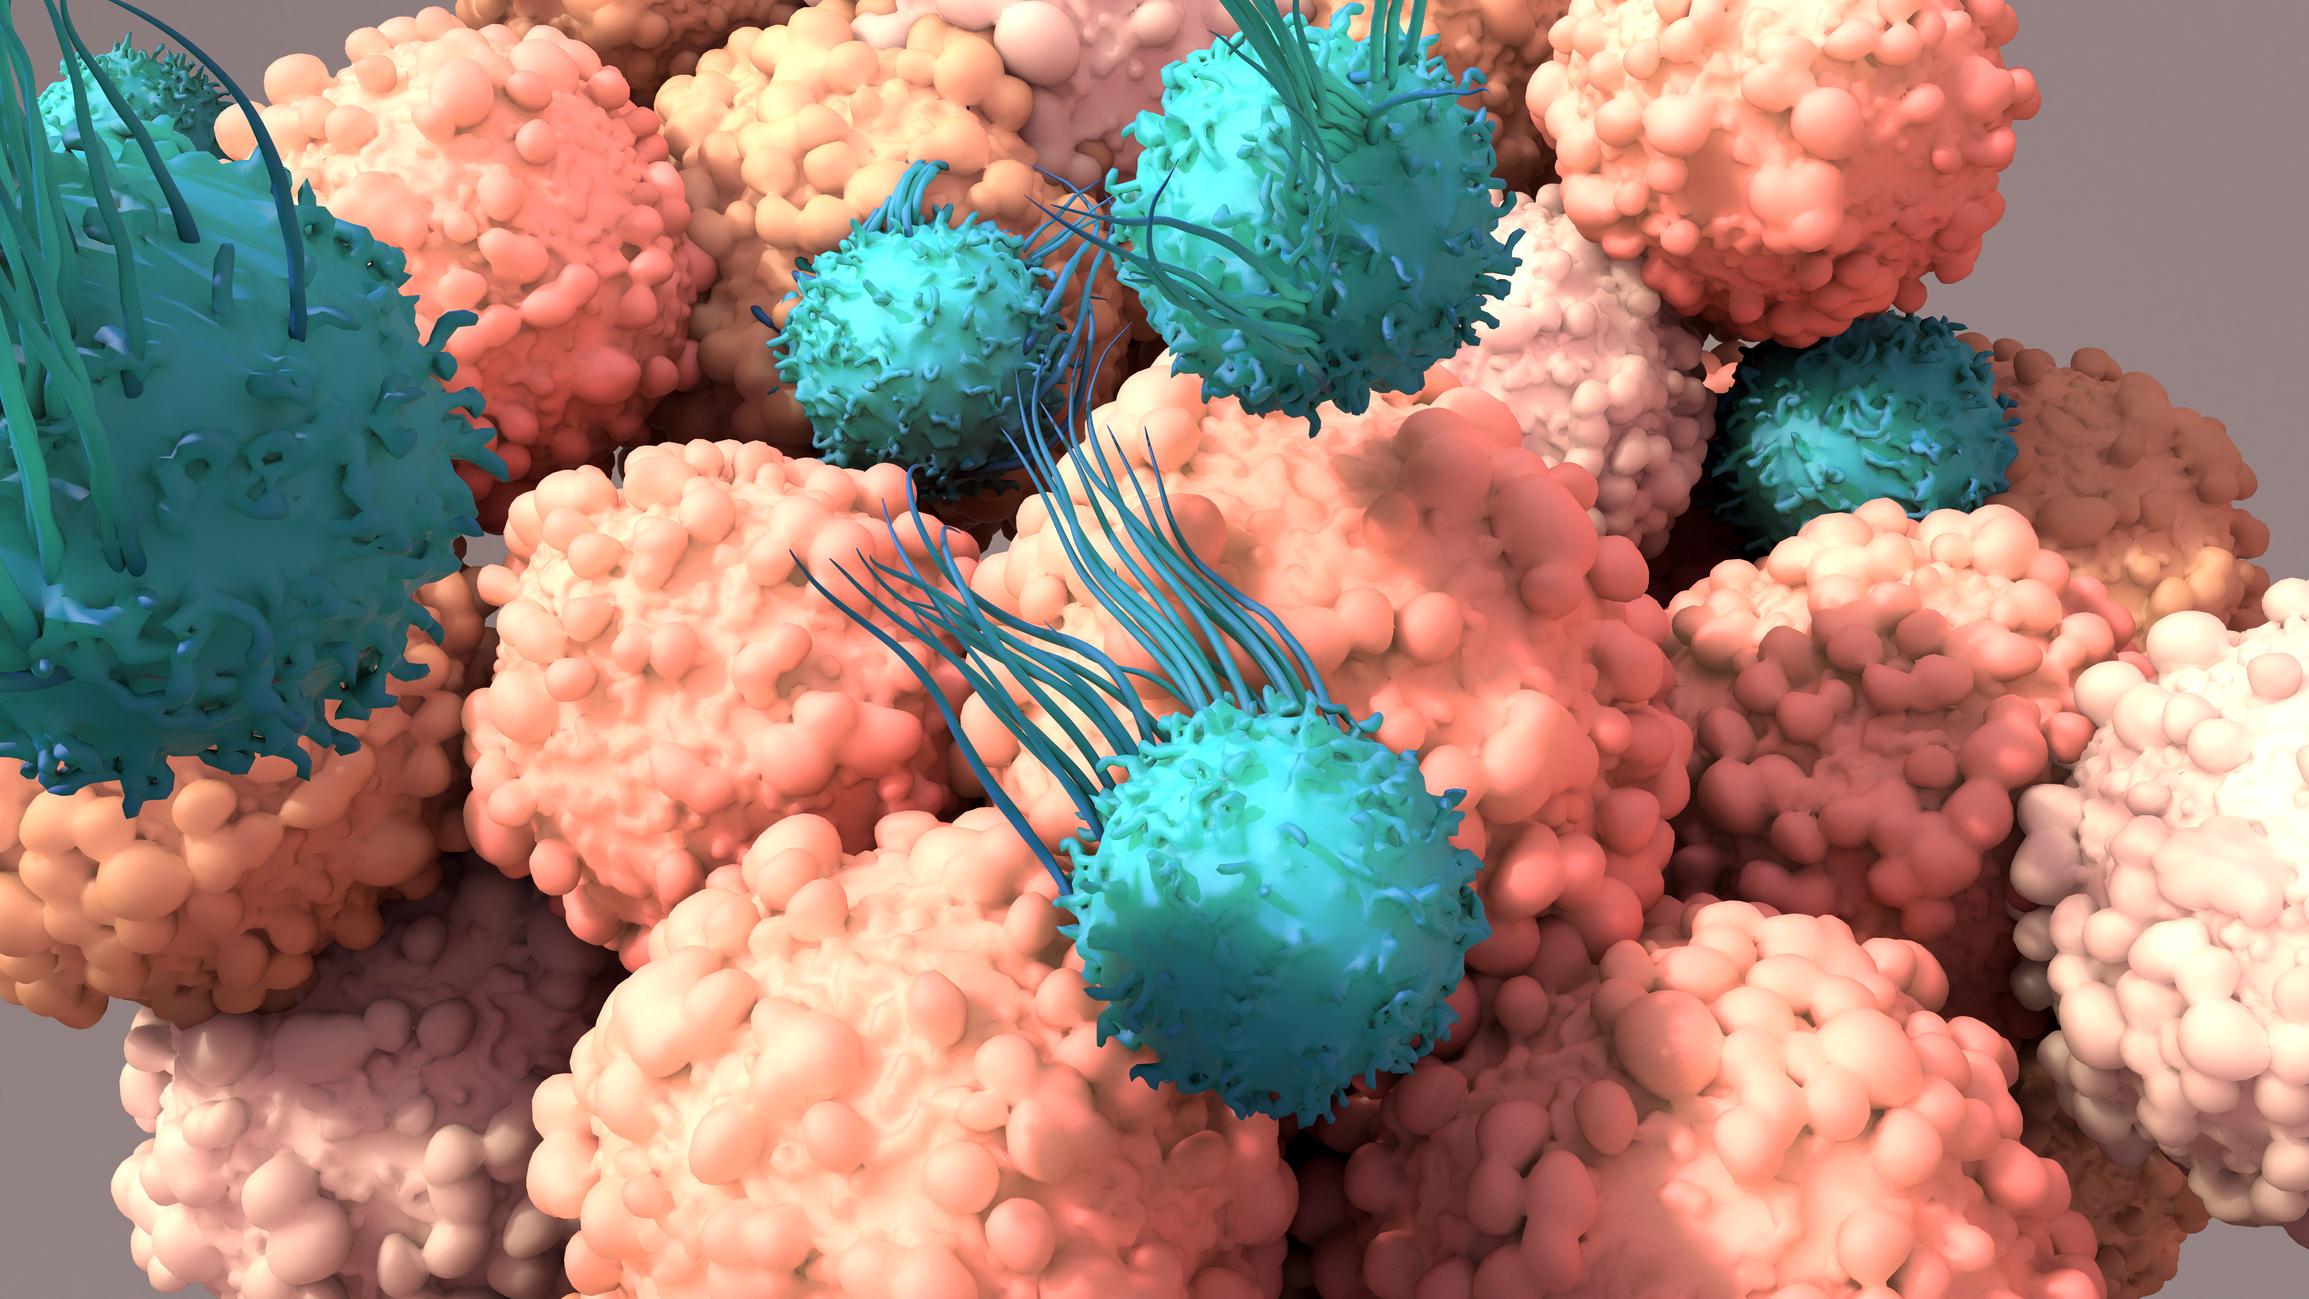
Over the past decade, cell and gene therapies have advanced at a remarkable pace, yet manufacturing remains a barrier standing between scientific promise and the patients who need it most. We can especially see this hurdle in allogeneic CAR-T for relapsed/refractory (R/R) T-cell malignancies, including T-cell acute lymphoblastic leukaemia and T-cell lymphoblastic lymphoma (T-ALL/LBL). Autologous CAR-T has already changed lives, delivering durable remissions for haematologic cancers to patients who were running out of options. But the quality that makes it personal, turning a patient’s own T-cells into a living drug, is also what makes it so hard to scale. Each product has to be made one patient at a time.
For T-cell malignancies, this is a challenge that cuts even deeper. It’s often difficult to tell a healthy T-cell from a malignant one, which makes both autologous and in vivo approaches hard to apply.
Allogeneic CAR-T, built from healthy donor T-cells, offers a different path toward scale, accessibility, and consistency. Immune-evasion engineering has allowed these approaches to achieve strong activity and long-lasting effects, with response rates well above what’s typically seen with older therapies in this setting. That progress raises a new possibility, an off-the-shelf cell therapy manufactured in advance, held in inventory, and ready the moment a patient needs it, sitting in the pharmacy the same way as a bottle of ibuprofen. What was once a theoretical workaround for the limits of autologous manufacturing is becoming a therapeutic category of its own.
Manufacturing bottlenecks in today’s cell & gene therapies ecosystem
Autologous CAR-T typically takes several weeks from cell collection to infusion, and a meaningful number of patients unfortunately don’t have enough healthy T-cells left to make a viable product, especially after multiple rounds of chemotherapy. Beyond that, the process depends on a chain of specialised logistics: apheresis at a qualified centre, cryopreserved shipment to a manufacturing site, individualised processing, and shipment back to the clinic. In other disease states, some patients never make it to infusion at all as their disease progresses too rapidly. Every link in this chain limits how many patients a site can reach and how far that access can extend, especially outside the US and in communities that are not equipped for patient-specific production.
For patients with rapidly progressing conditions, like R/R T-ALL/LBL, these delays aren’t just logistical; they carry a real clinical risk. For some, the disease outruns the timeline of manufacturing. For others, the wait leaves them too sick to receive therapy at all. That’s not just a bottleneck, it’s a constraint on how many patients can be reached, how quickly, and how consistently. That gap will only widen as cell therapy moves beyond R/R haematologic cancers into earlier lines of treatment and chronic autoimmune disease, patient populations a small-volume manufacturing model was never built to serve.
Why allogeneic CAR-T is a turning point for scalability
A single donor apheresis can generate multiple production batches, enough to make infusions for dozens of patients, and enough to supply an entire clinical study. This can shift the current industry model from per-patient production to batch manufacturing. The ability to batch manufacture creates immediate availability and consistent, well-characterised quality, bypassing the patient-specific bottlenecks that constrain autologous workflows. With this approach, there would be no need to wait for a manufacturing slot, no risk of insufficient starting material, and only a minimal delay between diagnosis and treatment. That same batch-produced model also extends accessibility beyond specialised academic centres, including regions outside the US that lack infrastructure for individualised cell processing.
This approach, however, does come with its own set of distinct challenges. Donor-derived cells are inherently foreign to the recipient’s immune system, and the body’s natural response is to reject them before they’ve had time to expand and eliminate the malignant cells. In order to manage this rejection risk, the response has been to increase the dose of lymphodepleting chemotherapy given before infusion, dampening the patient’s immune system so the CAR-T cells can survive and expand. While that approach helps with rejection, it does nothing for graft-versus-host disease (GvHD), the reverse problem where donor T-cells attack the patient’s own tissue. But that solution comes at a price. Higher lymphodepletion doses raise patient risk, bringing back the burden allogeneic therapy aims to spare patients from. Solving for scale, in other words, is only half the challenge; we also have to achieve safety and durability without bringing back the burdens allogeneic therapy was designed to remove.
The manufacturing innovations enabling allogeneic CAR-T at scale
Using gene-editing tools to knock out expression of the T-cell receptor and human leukocyte antigen class II genes eliminates the risk of GvHD and prevents host T-cell rejection, enabling a universal donor cell model that doesn’t require patient-specific matching. On top of that, immune-evasion engineering introduces inhibitory ligands that selectively dampen the host’s immune response to the CAR-T cell, without eliminating the patient’s immune system altogether. That reduction in immune rejection allows for the use of lower doses of lymphodepletion without sacrificing CAR-T expansion or persistence, a meaningful safety benefit that doesn’t come at the cost of efficacy.
The manufacturing process has to advance alongside the biology it’s built to support. Closed-system, semi-automated bioprocessing platforms could replace open, manual handling steps, shrinking the footprint, staffing, and cleanroom requirements needed to run a production campaign, while improving the lot-to-lot consistency that regulators expect from an off-the-shelf product. This batch-based approach has already demonstrated the capacity to generate an estimated 80 to 160 patient doses from a single donor apheresis, underscoring the scalability required for true off-the-shelf production.
These aren’t quick fixes; they’re the product of years of careful refinement. Immune-evasion technology has moved through several generations, now in its fifth iteration, with each generation bringing sharper editing precision and a deeper ability to validate safety and function. Meanwhile, advances in sequencing have made it easier to catch structural variations in genome-edited CAR-T cells, giving patients a more rigorous layer of safety assessment than earlier approaches offered.
Together, these innovations point to a broader shift taking hold across the cell therapy sector: a move from personalised, artisanal manufacturing toward scalable, standardised production, without losing the clinical performance that made autologous CAR-T a breakthrough in the first place. The question is no longer whether allogeneic can work; it’s how many patients it can reach, how quickly, and how consistently.
Remaining challenges and what the industry must solve next
Despite this progress, challenges and questions remain. The field still doesn’t have a full clinical picture of how allogeneic persistence and durability compare with autologous benchmarks over the long term, though ongoing trials are starting to fill that in. Balancing immune evasion with safety remains an ongoing challenge: minimising GvHD risk while keeping enough immune visibility for the therapy to keep working. And while lymphodepletion is still necessary, it can likely be scaled back further over time, sparing patients some of the toll and widening who can safely receive treatment.
Scaling up manufacturing carries its own risks, too. Moving from clinical-scale to commercial-scale batch production means proving that potency, purity, and safety hold up consistently across larger, more numerous lots, and under the messier conditions of real-world supply chains, rather than the tightly controlled conditions of early clinical manufacturing. Donor sourcing and manufacturing capacity need redundancy built in as well, so a single site or supply disruption can’t cut off patients who are counting on this therapy.
Beyond the science, there’s structural work ahead, too. Global regulatory alignment around engineered donor-cell products is still a work in progress across major markets, and registration pathways and geographic trial expansion are still taking shape industry-wide. Earning the confidence of physicians and payers in off-the-shelf cell therapy will take continued, rigorous clinical validation across both oncology and emerging autoimmune conditions.
The path forward: Building a scalable foundation for the next era of cell therapies
Allogeneic CAR-T represents a real chance to widen access to cell therapy, especially for patients whose disease can’t wait for the weeks that bespoke autologous manufacturing requires. Realising that chance depends on manufacturing strategies that bring together standardisation, continued engineering innovation, and rigorous clinical validation.
It also means manufacturing has to be part of the design from the start, not an afterthought added once a therapy proves itself in the clinic. Companies that design for manufacturability alongside potency and safety are the ones best positioned to turn early clinical signals into therapies that reach patients wherever they’re needed, not just the academic centres where those therapies were first discovered.
The path to allogeneic CAR-T products with autologous-level performance and off-the-shelf speed is coming into view. Getting there will require sustained innovation, cross-industry collaboration, and disciplined scientific evaluation. But the route is clear, and the patients waiting on the other side of that progress are what make the effort worth it.
About the author
 Lu Han is founder & CEO of ImvivaBio, a global biotech advancing allo CAR-T therapies in oncology and autoimmune diseases. He leads corporate strategy, BD, capital formation, early clinical development, and global expansion. Han brings 10+ years of healthcare entrepreneurship and company-building experience, having founded and scaled two healthcare companies, both of which have operated for nearly a decade. Earlier in his career, he worked across finance and global life sciences, including HSBC IBD, Morgan Stanley PE, and Lonza’s Basel HQ, where he focused on internal audit. Han holds an MSc in Finance and a BSc in Biological Science.